
Limited-Time Offer: Enjoy 50% Savings! Ends in 00h 00m 00s Coupon code: 50OFF
Skip to content

Free NAHQ Certified Professional in Healthcare Quality CPHQ Exam Questions

Page: 1 / 46 Total 685 questions

Want more questions? Get Premium Access.

Question 1

A quality professional is leading a rapid process improvement event to reduce central line infections. Which of the following actions should be taken?

Correct Answer: C. Review the Agency for Healthcare Research and Quality for relevant resources
Explanation:

A rapid process improvement event (e.g., Kaizen) focuses on quick, targeted interventions to improve a specific process, such as reducing central line-associated bloodstream infections (CLABSIs).

Option A (Design indicators for hospital-wide data collection plan): Designing indicators is a long-term strategy, not suited for a rapid event, which focuses on immediate process changes.

Option B (Search the United States Preventive Services Taskforce for recommendations): USPSTF provides preventive care guidelines, not specific hospital infection control strategies like CLABSIs.

Option C (Review the Agency for Healthcare Research and Quality for relevant resources): This is the correct answer. The NAHQ CPHQ study guide states, ''AHRQ provides evidence-based resources, such as toolkits for reducing CLABSIs, that are practical for rapid improvement events'' (Domain 4). AHRQ's CLABSI toolkit offers actionable protocols for rapid implementation.

Option D (Conduct a systematic review of studies in intensive care units): Systematic reviews are time-intensive and not feasible for a rapid event, which prioritizes quick action over exhaustive research.

CPHQ Objective Reference: Domain 4: Performance and Process Improvement, Objective 4.4, ''Use evidence-based resources for improvement initiatives,'' highlights AHRQ as a key source for practical tools. The NAHQ study guide notes, ''AHRQ toolkits are ideal for rapid process improvement events due to their evidence-based, ready-to-use protocols'' (Domain 4).

Rationale: AHRQ's CLABSI resources provide immediate, evidence-based strategies for a rapid improvement event, aligning with CPHQ's focus on actionable interventions.
Question 2

Which of the following is the strongest intervention for preventing medication safety events?

Correct Answer: D. Creating a hard stop for allergy documentation prior to ordering medications
Explanation:

Preventing medication safety events requires interventions that are robust, systemic, and difficult to bypass, particularly for critical safety checks.

Option A (Adding colored warning labels to high-risk medications): Labels are helpful but rely on human vigilance, which can fail, making them less strong.

Option B (Educating providers on accurate medication reconciliation): Education is important but less effective than system-based interventions, as it depends on compliance.

Option C (Limiting the number of medication warnings triggered in the electronic health record): Reducing warnings may decrease alert fatigue but risks missing critical alerts, weakening safety.

Option D (Creating a hard stop for allergy documentation prior to ordering medications): This is the correct answer. The NAHQ CPHQ study guide states, ''Hard stops in electronic health records, such as requiring allergy documentation before medication orders, are the strongest interventions for preventing errors by enforcing compliance'' (Domain 1). Hard stops prevent progression without action, ensuring safety.

CPHQ Objective Reference: Domain 1: Patient Safety, Objective 1.4, ''Implement system-based safety interventions,'' emphasizes hard stops for critical processes. The NAHQ study guide notes, ''Hard stops are highly effective for enforcing safety protocols like allergy checks'' (Domain 1).

Rationale: Hard stops create an unavoidable barrier to errors, making them the strongest intervention, as per CPHQ's patient safety principles.


Question 3

In an aging population, one of the challenges associated with the use of practice guidelines is

Correct Answer: D. most practice guidelines only address a single issue, not multiple co-morbidities.
Explanation:

In an aging population, one of the significant challengesassociated with the use of practice guidelines is that most practice guidelines only address a single issue and do not consider the multiple co-morbidities that are common in older patients. As the population ages, patients often have complex health needs that involve several chronic conditions simultaneously. Single-issue guidelines may not adequately address these complexities, leading to potential gaps in care.

The cost of instructions to implement new guidelines increases yearly (A): While costs may be a concern, the primary challenge in an aging population is addressing co-morbidities.

The constant evolution of healthcare makes it difficult to keep practice guidelines relevant (B): This is a challenge, but it applies broadly, not specifically to the aging population.

Changing behavior to improve care is a complex process (C): This is true but is a broader challenge that applies to many aspects of healthcare improvement, not specifically to the aging population.

Reference

NAHQ Body of Knowledge: Challenges in Implementing Practice Guidelines

NAHQ CPHQ Exam Preparation Materials: Practice Guidelines and Comorbidities


Question 4

The quality improvement tool used to identify special-cause variation in a process is a:

Correct Answer: D. Control Chart
Explanation:

Detailed

Special-cause variation represents unexpected deviations due to specific circumstances and can be identified using controlcharts.

Option D: Control Chart

Control charts are designed to distinguish between common-cause and special-cause variations, using control limits to flag unusual patterns.

Option C: Run Chart

Run charts show trends but lack control limits to distinguish special-cause variation.

Options A and B:

Pareto charts and flowcharts categorize and map issues or processes, respectively, without indicating special-cause variation.


CPHQ materials emphasize control charts for identifying special causes, as they provide statistical boundaries essential for quality control.

Question 5

A multidisciplinary team has been convened to review delays in laboratory turnaround time between the medicine clinic and the laboratory. The team's first step in evaluating the issue is to

Correct Answer: A. create a flow chart to study the process.
Explanation:

The first step for a multidisciplinary team tasked with evaluating delays inlaboratory turnaround time is to create a flow chart to study the process. A flow chart visually maps out the steps involved in the current process, allowing the team to understand each stage, identify bottlenecks, and pinpoint where delays might be occurring. This provides a clear, shared understanding of the process among all team members, which is essential before diving into more detailed analysis or improvements.

Conduct a failure mode and effects analysis (FMEA) (B): FMEA is a valuable tool for identifying potential failures, but it is typically used after understanding the process in detail.

See if the surgery clinic is also experiencing delays (C): While this could be useful information, the primary focus should be on the specific process under review.

Observe how the medical assistants prepare the specimens (D): Observation is important, but understanding the entire process flow is the first step.

Reference

NAHQ Body of Knowledge: Process Mapping and Flowcharting in Quality Improvement

NAHQ CPHQ Exam Preparation Materials: Initial Steps in Process Improvement


Question 6

Which of the following Is the best approach to prepare care team members tor Interacting with accreditation surveyors?

Correct Answer: C. Brief them on survey activities and what questions to expect.
Explanation:

Preparing care team members for interacting with accreditation surveyors is a crucial part of the accreditation process. The best approach is to brief them onsurvey activities and what questions to expect (Option C).This involves providing them with an understanding of the survey objectives, the day's schedule, and the types of questions that surveyors may ask1. This approach helps to ensure that team members are well-prepared and confident when interacting with surveyors. Reviewing patient records proactively (Option A) and summarizing and discussing past survey findings (Option B) can also be helpful, but these activities are more focused on identifying and addressing potential issues before the survey, rather than preparing team members for the survey itself. Providing techniques to defer surveyor questions to leaders (Option D) could potentially create a perception of lack of transparency or evasion, which could negatively impact the survey results.


https://www.jointcommission.org/what-we-offer/accreditation/health-care-settings/laboratory-services/prepare/prepare-support/8-best-practices-to-prepare-for-the-survey/

Question 7

Several leaders in a healthcare facility have differing opinions regarding the pursuit of alternative certifications and recognitions. The Chief Quality Officer (CQO) has opted to retain an external quality consultant to determine relevance, appropriateness, and readiness for an alternative certification. The most appropriate role for an external consultant is to

Correct Answer: A. evaluate the facility's needs, goals, and stakeholder input.
Explanation:

An external quality consultant provides objective, expert analysis to guide decision-making in organizational leadership initiatives. The most appropriate role is to evaluate the facility's needs, goals, and stakeholder input (A), ensuring alignment with strategic priorities and readiness. Determining the final certification (B), uncovering other opportunities (C), or supporting the CQO's choice (D) are not the consultant's primary roles. NAHQ emphasizes objective assessment in leadership decisions.

: NAHQ CPHQ Study Guide, Organizational Leadership Section, ''Role of External Consultants in Quality Initiatives''; NAHQ Code of Practice, Principle 2: Strategic Leadership.


Question 8

A healthcare quality professional has been hired to assist a quality improvement team with data analysis. In an attempt to enhance the team's analysis of the data, the quality professional should

Correct Answer: A. Use visual, graphical methods to present the data
Explanation:

Effective data analysis in quality improvement requires presenting data in a way that is clear, actionable, and easily understood by the team.

Option A (Use visual, graphical methods to present the data): This is the correct answer. The NAHQ CPHQ study guide states, ''Visual, graphical methods (e.g., charts, graphs) enhance data analysis by making trends and patterns clear to quality improvement teams'' (Domain 2). Tools like run charts or Pareto charts aid decision-making.

Option B (Collect and present all the completed data collection tools): Presenting raw tools (e.g., surveys) is cumbersome and less effective than summarizing data visually.

Option C (Publish and disseminate raw data in tables): Raw data tables are difficult to interpret and less actionable than graphical displays.

Option D (Direct the team to collect as much data as possible): Collecting excessive data without analysis is inefficient and may overwhelm the team.

CPHQ Objective Reference: Domain 2: Health Data Analytics, Objective 2.3, ''Select appropriate data display tools,'' emphasizes visual methods for effective analysis. The NAHQ study guide notes, ''Graphical displays improve team understanding and engagement with data'' (Domain 2).

Rationale: Visual methods make data accessible and actionable, aligning with CPHQ's focus on data-driven quality improvement.


Question 9

When planning a healthcare organization's performance improvement training, the curriculum is developed considering the needs of which groups?

Correct Answer: A. Senior leaders, middle managers, and frontline staff
Explanation:

Performance improvement (PI) training equips staff to participate in quality initiatives, requiring a curriculum tailored to the roles and responsibilities of those directly involved in care delivery and management.

Option A (Senior leaders, middle managers, and frontline staff): This is the correct answer. The NAHQ CPHQ study guide states, ''Performance improvement training should be designed to meet the needs of senior leaders (strategic oversight), middle managers (implementation), and frontline staff (execution of processes)'' (Domain 3). These groups are critical for driving and sustaining PI initiatives, as they represent the organizational hierarchy responsible for quality improvement.

Option B (Insurance companies, Medicare, and Medicaid): These are external payers, not internal groups requiring PI training. Their role is in reimbursement, not organizational improvement processes.

Option C (Licensure, certification, and accrediting agencies): These entities set standards but are not trained by the organization. They assess compliance, not participate in PI.

Option D (The governing body and external stakeholders): The governing body provides oversight, and external stakeholders (e.g., community partners) may be informed, but they are not the primary focus of PI training, which targets internal staff.

CPHQ Objective Reference: Domain 3: Organizational Leadership, Objective 3.3, ''Develop and implement training programs to support performance improvement,'' emphasizes tailoring training to internal stakeholders like leaders, managers, and staff to ensure effective PI adoption. The NAHQ study guide highlights the need for role-specific training to address the unique contributions of each group.

Rationale: Senior leaders set PI priorities, middle managers coordinate initiatives, and frontline staff implement changes. Training must address their distinct needs to ensure alignment and success, as outlined in CPHQ leadership principles.


Question 10

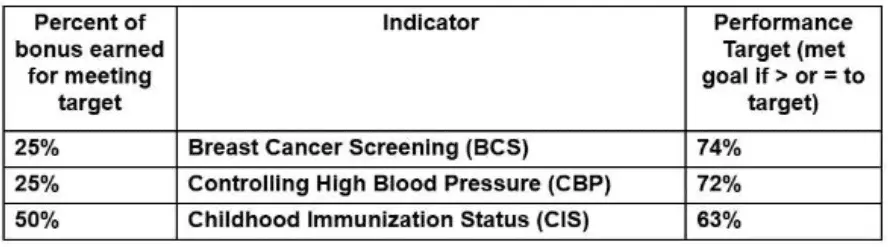
Each provider in a primary care practice has the potential of earning a $20,000 bonus based on individual performance on select Healthcare Effectiveness Data and Information Set (HEDIS) indicators as outlined below:

Based on this information, which of the following conclusions is accurate?

Correct Answer: D. Provider C earned the highest bonus.
Explanation:

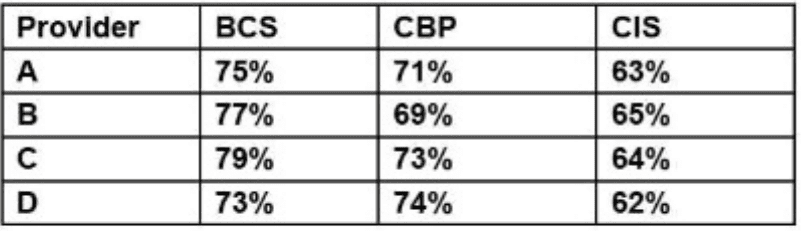
To calculate the bonus, evaluate whether each provider met the performance targets for each HEDIS indicator and multiply by the corresponding percentage of the $20,000 bonus.

Provider A:

BCS: 75% 74% 25% of $20,000 = $5,000

CBP: 71% < 72% $0

CIS: 63% 63% 50% of $20,000 = $10,000

Total = $15,000

Provider B:

BCS: 77% 74% $5,000

CBP: 69% < 72% $0

CIS: 65% 63% $10,000

Total = $15,000

Provider C:

BCS: 79% 74% $5,000

CBP: 73% 72% $5,000

CIS: 64% 63% $10,000

Total = $20,000

Provider D:

BCS: 73% < 74% $0

CBP: 74% 72% $5,000

CIS: 62% < 63% $0

Total = $5,000

Provider C earned the highest bonus at $20,000, meeting or exceeding all three performance targets. Provider D earned the lowest bonus, $5,000, meeting only the CBP target.


National Committee for Quality Assurance (NCQA), HEDIS Technical Specifications, 2024

The Joint Commission, Performance Improvement Standards, 2024

Question 11

A physician challenges the number of healthcare-acquired infections reported for orthopedic surgery. Which of the following will be most effective in demonstrating the validity of the information?

Correct Answer: B. criteria used to classify infections
Explanation:

When a physician challenges the reported number of healthcare-acquired infections (HAIs), the most effective way to demonstrate data validity is to provide transparency into the methodology used to identify and classify infections. NAHQ CPHQ study materials emphasize that standardized criteria, such as those from the CDC National Healthcare Safety Network (NHSN), are used to define HAIs. Sharing the criteria used to classify infections (B) addresses concerns about accuracy and consistency. Options A, C, and D do not directly validate the infection counts.

: NAHQ CPHQ Study Guide, Patient Safety Section, ''Healthcare-Acquired Infections and Data Validation''; NAHQ CPHQ Practice Exam, Patient Safety Metrics and Reporting.


Question 12

Data from an incident reporting system compares incident rates for one facility to similar facilities:

After reviewing the graph, which of the following should be done first?

Correct Answer: C. Perform additional analysis on falls data.
Explanation:

Detailed

When comparing incident rates across facilities, it's important to focus first on areas with potentially higher risk or impact. A logical first step is to conduct a deeper analysis of the specific data type or area that stands out as problematic. Here's the rationale for each option:

Option C: Perform additional analysis on falls data

Incident rates, especially if the data indicates a high or concerning trend (e.g., an unusual increase in falls), should beprioritized. Further analysis can provide insights into patterns, causes, and potential preventive strategies. Understanding specific issues around falls helps guide targeted interventions, aligning with CPHQ guidance on data-driven problem-solving.

Option A: Research best practices

This is a valuable step, but it would be more useful after pinpointing which areas require improvement through focused analysis. Best practices should address specific issues identified from detailed data reviews.

Option B: Share data with the governing body

Although sharing data is important, doing so prematurely without thorough internal analysis might hinder effective communication. The governing body should ideally receive a report containing analyzed data andproposed actions.

Option D: Review medication processes

Reviewing medication processes is beneficial, but unless the incident data specifically indicates a medication-related issue, this would not be the initial focus.


This approach aligns with CPHQ principles on data analysis for quality improvement, as well as root cause analysis (RCA) methods, which prioritize analyzing specific trends before taking action.

Question 13

A patient safety manager provided training on hand hygiene guidelines. The clinical manager Is confident that staff are following the guidelines. Which of the following Is the best method to evaluate the current compliance with the guidelines?

Correct Answer: B. direct observation of staff
Explanation:

According to the WHO Guidelines on Hand Hygiene in Health Care, direct observation of hand hygiene practices is the gold standard for measuring compliance1.Direct observation allows for the assessment of the five moments of hand hygiene, the use of appropriate technique, and the identification of barriers and facilitators to adherence1.

Direct observation also provides an opportunity for immediate feedback and education to the health care workers, which can improve their knowledge and motivation to perform hand hygiene2.Direct observation can be done covertly or overtly, depending on the purpose and context of the audit2.

Other methods of measuring hand hygiene compliance, such as collection of bacterial hand cultures, calculation of infection rates, or a test with a passing score, have limitations and disadvantages.For example, bacterial hand cultures may not reflect the actual transmission of pathogens, infection rates may be influenced by many factors other than hand hygiene, and a test score may not correlate with actual behavior2.Reference:1: WHO Guidelines on Hand Hygiene in Health Care, WHO, 20092: Hand Hygiene:Education, Monitoring and Feedback, CDC, 2019


Question 14

Which of the following is the best method of determining improvement priorities to benefit the health of the community?

Correct Answer: B. Needs assessment survey
Explanation:

Detailed

A needs assessment survey systematically identifies community health needs, helping prioritize interventions based on specific gaps and requirements.

Option B: Needs assessment survey

A needs assessment is a structured approach to determine priorities by collecting input from community members, ensuring interventions are relevant.

Options A, C, and D:

Focus groups provide insights but may lack comprehensive coverage.

Windshield surveys and census reviews offer observational data but do not capture specific needs.


CPHQ study materials recommend needs assessments for understanding community health priorities comprehensively.

Question 15

Which of the following actions best demonstrates that an organization has begun the work necessary to achieve the Malcolm Baldrige award?

Correct Answer: D. reviewing the Malcolm Baldrige standards to determine organization alignment
Explanation:

The Malcolm Baldrige National Quality Award is the highest level of national recognition that a U.S.organization can receive for performance excellence1.The award criteria focus on eight performance dimensions: Leadership and Governance, Strategy, Operations, Operational Continuity, Workforce, Customers and Markets, Community Engagement, and Finance1.

To achieve the Malcolm Baldrige award, an organization must demonstrate organizationalresilience and long-term success through favorable performance levels and trends, comparisons to competitors and industry benchmarks (as appropriate), and relevant metrics1. Therefore, reviewing the Malcolm Baldrige standards to determine organization alignment is the best demonstration that an organization has begun the work necessary to achieve the Malcolm Baldrige award.

While creating a team to revise operations to conform to the Malcolm Baldrige requirements (Option A) is a step in the process, it does not necessarily demonstrate that the organization has begun the work necessary to achieve the award. The same applies to developing a crosswalk between Malcolm Baldrige and Joint Commission requirements (Option B) and determining effects on CMS Conditions of Participation (Option C). These actions could be part of the process, but they do not directly demonstrate that the organization has begun the work necessary to achieve the Malcolm Baldrige award.

Beginning work toward achieving the Malcolm Baldrige National Quality Award necessitates a comprehensive understanding of the criteria and how an organization currently aligns with them. This would involve a thorough review of the Baldrige Excellence Framework, which includes the standards for performance excellence. By assessing current practices against the Baldrige criteria, an organization can identify areas of strength and opportunities for improvement. This review serves as a foundational step in theBaldrige journey, guiding the development of a detailed action plan to address gaps and enhance performance.